
Apolipoprotein B (ApoB)
Updated October 31, 2026 · 39 sources · Written by the AumniVIDA team
UnitsWhat is ApoB?
ApoB (apolipoprotein B) is the protein on every LDL, VLDL, IDL and Lp(a) particle, one per particle, so a blood ApoB test counts the particles that drive atherosclerosis. The US median is 90 mg/dL (0.90 g/L)0.90 g/L (90 mg/dL); European goals are under 100, 80 or 65 mg/dL depending on risk.
Questions people ask about ApoB
- 01ApoB test: how to measure it, what it costs and how to prepareAn ApoB test is a standard blood draw that counts atherogenic particles. You do not need to fast. Guidelines suggest it most when triglycerides are high, with diabetes or obesity, or when LDL-C is very low on treatment. Results come in mg/dL or g/L, and experts suggest retesting 4 to 12 weeks after a treatment change.Read the answer
- 02How to lower ApoBMedications lower ApoB the most: PCSK9 inhibitors by 43 to 50 percent, statins by about 33 percent, and bempedoic acid or added ezetimibe by about 14 to 15 percent. Diet changes each lower it by a few mg/dL: psyllium by 5, walnuts by 4, oat beta-glucan by 3. Cutting saturated fat helps too.Read the answer
- 03What does a high ApoB mean?A high ApoB means more cholesterol-carrying particles are circulating, and more can lodge in the artery wall.Read the answer
- 04What is a normal ApoB level?The median ApoB in US adults not on lipid drugs is 90 mg/dL (0.90 g/L)0.90 g/L (90 mg/dL), and labs flag 100 mg/dL (1.0 g/L)1.0 g/L (100 mg/dL) or higher.Read the answer
- 05ApoB vs LDL cholesterol: which matters more?ApoB counts all atherogenic particles; LDL cholesterol measures the cholesterol inside LDL particles.Read the answer
- 06ApoB vs Lp(a): what is the difference?ApoB counts every atherogenic particle, Lp(a) included.Read the answer
Key takeaways
- 1
ApoB counts atherogenic particles directly, because each LDL, VLDL, IDL and Lp(a) particle carries exactly one ApoB [1].
- 2
Genetic studies show heart disease risk falls by the same amount per 10 mg/dL of ApoB lowered, whether triglycerides or LDL-C fall [2].
- 3
- 4
ApoB adds the most when triglycerides are high, with diabetes or obesity, or when LDL-C is very low on treatment [3].
- 5
You do not need to fast for an ApoB test [5].
- 6
No trial has yet compared ApoB-guided treatment with LDL-C-guided treatment [6].
What is ApoB?
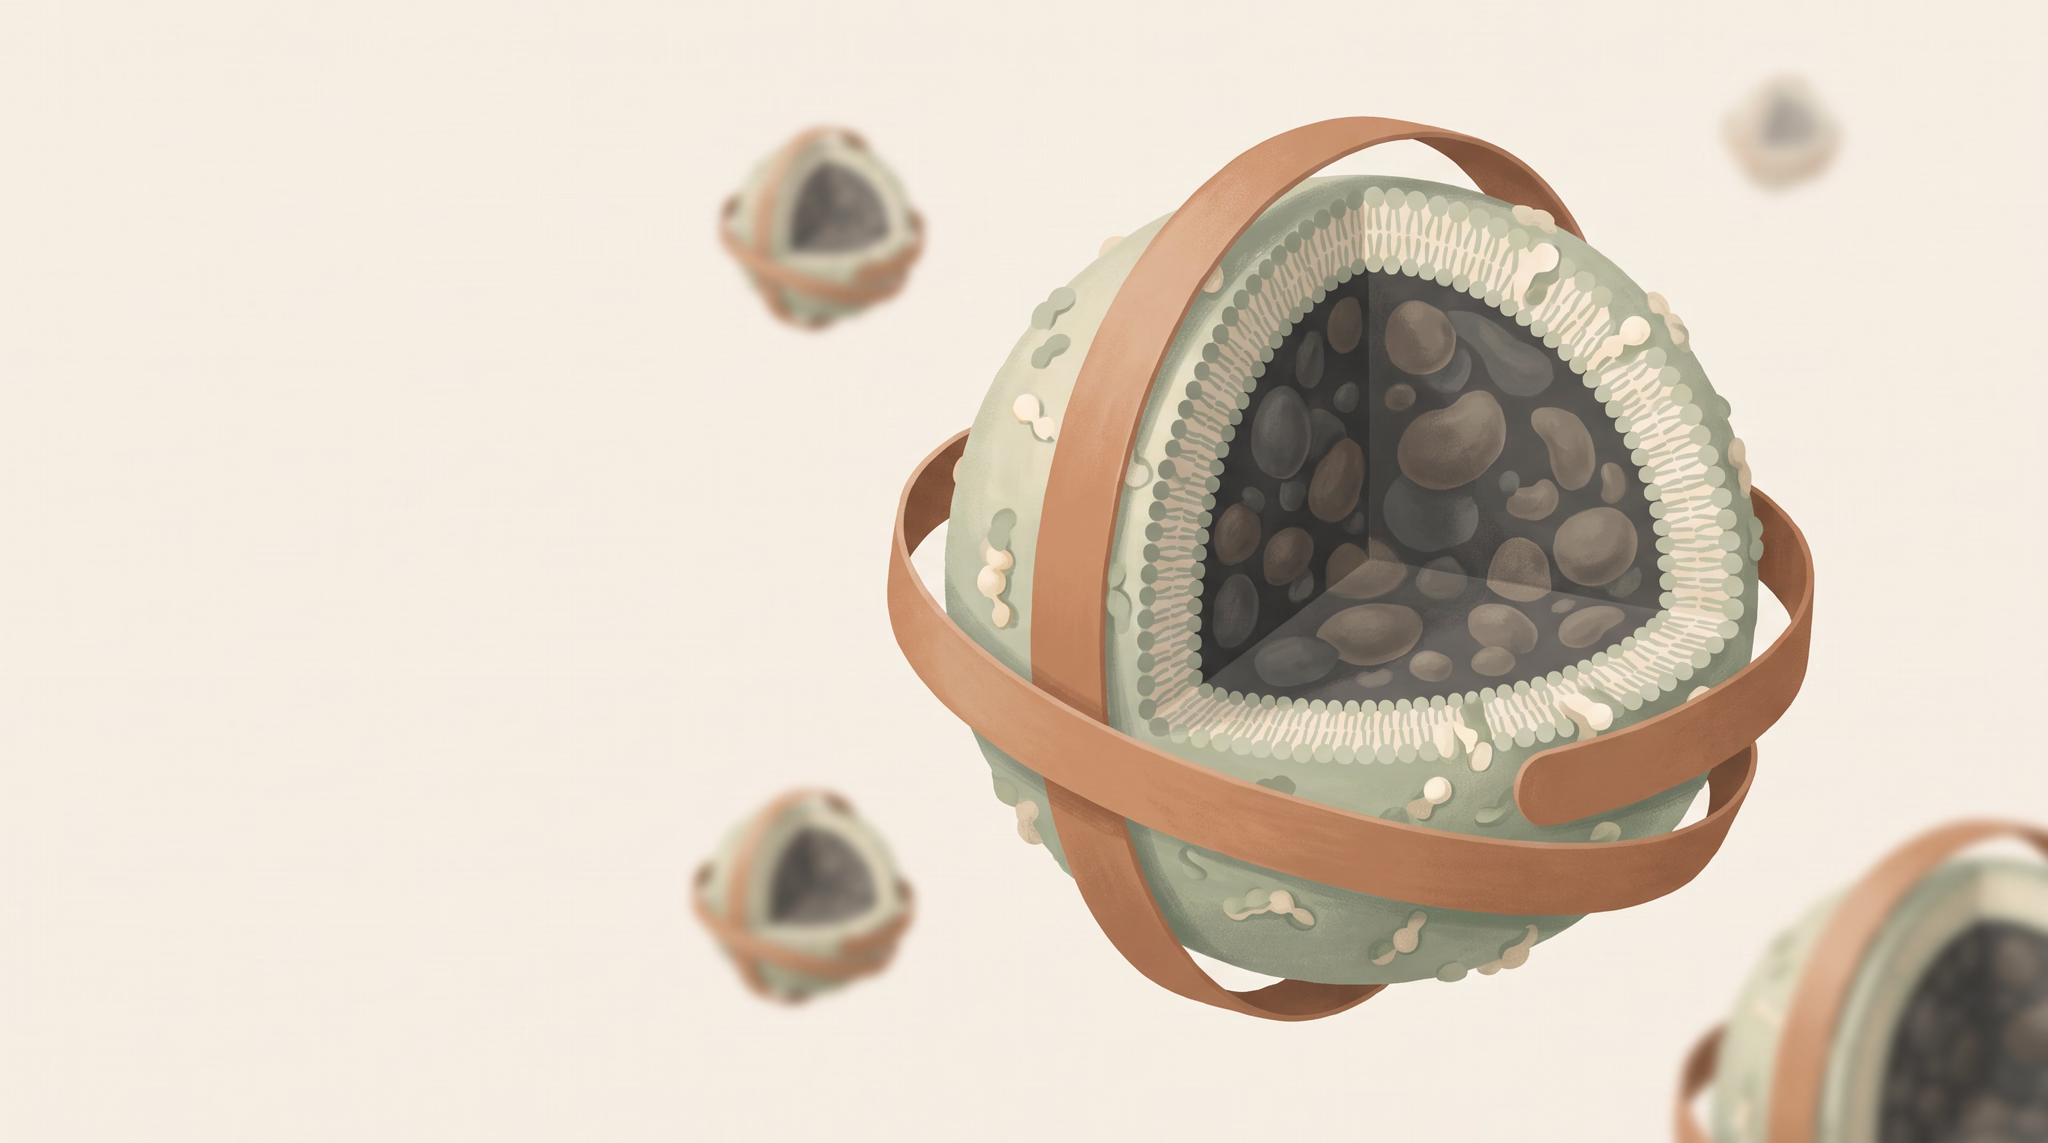
ApoB, short for apolipoprotein B, is the structural protein of every particle that can carry cholesterol into the artery wall. Each of those particles carries exactly one ApoB molecule, so the ApoB blood test is a direct count of them.
Cholesterol and triglycerides do not dissolve in blood. They travel inside lipoproteins: small spheres with a fatty core and a protein-studded shell. The particles that cause atherosclerosis (LDL, VLDL, IDL, Lp(a) and chylomicron remnants) all carry one copy of ApoB, which holds the particle together and lets the liver clear it [1].
Because the ratio is one to one, the ApoB concentration in your blood equals the concentration of these particles [1]. That is the core idea behind the test. A standard lipid panel tells you how much cholesterol the particles carry. ApoB tells you how many particles there are.
Labs report ApoB in mg/dL in the US or g/L in Europe and Canada. To convert, divide mg/dL by 100: 90 mg/dL is 0.90 g/L. The median for US adults not taking lipid drugs is 90 mg/dL [1]. See what a normal ApoB level is for the full distribution.

What does ApoB do in the body?
ApoB builds and labels the particles that deliver fat and cholesterol around the body. The liver makes the full-length ApoB-100 for VLDL, IDL, LDL and Lp(a); the gut makes a shorter ApoB-48 for chylomicrons that carry dietary fat.
ApoB-100 is one of the largest proteins in the blood: its precursor is 4,563 amino acids long [7]. The liver wraps each new VLDL particle in one ApoB-100. As VLDL gives up triglyceride to muscle and fat tissue, it shrinks into IDL and then LDL, keeping the same ApoB the whole way. A region of ApoB-100 rich in basic amino acids binds the LDL receptor, which is how the liver pulls LDL back out of the blood [7].
The intestine uses the same gene but edits the RNA: a single C to T change creates a stop signal at codon 2153, producing ApoB-48, about half the length [8]. ApoB-48 lacks the receptor-binding region and rides on chylomicrons, which carry fat from a meal [1].
Some people inherit a faulty ApoB. In familial defective ApoB-100, LDL particles bind the receptor at about a third of normal strength, so they stay in the blood longer and LDL rises [9]. This is one of the genetic causes of familial hypercholesterolemia, alongside LDL receptor and PCSK9 variants.
Not all ApoB particles are equally common. In one large cohort, LDL made up about 91 percent of ApoB particles and VLDL about 9 percent [10]. Chylomicrons carrying ApoB-48 are typically under 1 percent, even after a meal [3]. Lp(a) is a small share: in UK Biobank, mean ApoB was about 1,870 nmol/L and mean Lp(a) about 45 nmol/L [11], so Lp(a) is roughly 2 percent of particles on average, with wide variation between people.
| Particle | ApoB form | Made in | Main cargo | Share of ApoB particles |
|---|---|---|---|---|
| LDL | ApoB-100 | Formed from VLDL in blood | Cholesterol ester | About 91% |
| VLDL and IDL | ApoB-100 | Liver | Triglyceride, then cholesterol | About 9% |
| Lp(a) | ApoB-100 plus apo(a) | Liver | Cholesterol ester, oxidized phospholipids | About 2% on average, varies widely |
| Chylomicrons and remnants | ApoB-48 | Intestine | Dietary triglyceride | Under 1%, even after meals |
| HDL | None | Liver and intestine | Cholesterol returning to the liver | Not counted |
Why does ApoB matter for heart disease?
Atherosclerosis starts when ApoB particles slip into the artery wall and get stuck. The more particles in the blood, the more get trapped. Genetic studies and drug trials agree that the benefit of lowering blood lipids tracks the drop in ApoB.
Cholesterol only enters the artery wall inside ApoB particles, and the number of particles that become trapped depends mainly on how many are in the bloodstream [12]. That makes particle number, not just cholesterol content, the natural measure of exposure.
The causal evidence comes from three directions.
- Consensus on LDL. The European Atherosclerosis Society reviewed over 200 studies with more than 2 million people and concluded that LDL causes atherosclerotic disease, with risk rising with both the level and the years of exposure [13].
- Mendelian randomization. Genes that lower triglycerides and genes that lower LDL-C reduced coronary risk by the same amount, an odds ratio of 0.77, for every 10 mg/dL lower ApoB, in 654,783 people. Once ApoB was accounted for, triglycerides and LDL-C added nothing [2]. A separate multivariable analysis found ApoB was the lipid trait that explained the link with coronary disease [14].
- Observational head-to-head studies. Across 12 studies with 233,455 people, the relative risk per standard deviation was 1.43 for ApoB, 1.34 for non-HDL-C and 1.25 for LDL-C [15]. In UK Biobank, when ApoB, non-HDL-C and triglycerides were tested together, only ApoB stayed linked to heart attack [16]. Total particle count captured lipid risk regardless of whether the particles were LDL or VLDL, large or small [10].
Earlier cohort work pointed the same way. In the Swedish AMORIS study, ApoB predicted fatal heart attack better than LDL-C in both sexes [17]. In INTERHEART, across 52 countries, the ApoB/ApoA1 ratio carried the largest population attributable risk of any factor, 49 percent [18].
For what a high result means for you, see what a high ApoB means.
How ApoB became a guideline marker
1986
Full ApoB-100 sequence published
1987
Gut RNA editing explains ApoB-48
1987
Familial defective ApoB-100 described
2001
AMORIS: ApoB beats LDL-C for fatal heart attack
2004
INTERHEART: ApoB/ApoA1 ratio tops risk factors
2011
Meta-analysis ranks ApoB above non-HDL-C and LDL-C
2016
EAS/EFLM: no fasting needed
2017
EAS consensus: LDL causes atherosclerosis
2018
AHA/ACC: ApoB 130 mg/dL is a risk enhancer
2019
ESC/EAS ApoB goals; genetics tie benefit to ApoB
2020
Multivariable MR: ApoB is the driving trait
2021
Canada adds ApoB treatment thresholds
2024
NLA ApoB consensus; Lp(a) 6 times LDL per particle
2025
Particle count beats particle type
2026
ACC/AHA guideline adds selective ApoB testing
How is ApoB measured?
ApoB is measured from a normal blood sample with an automated antibody test that most clinical labs already run. You do not need to fast. The test is accurate, cheap for labs to perform, and often ordered alongside a standard lipid panel.
Commercial ApoB assays use antibodies (immunoturbidimetric or immunonephelometric methods) on the same analyzers that run routine lipid panels. Bias for most assays is below 4 mg/dL, and the coefficient of variation is usually 5 to 6 percent [1]. Unlike calculated LDL-C, ApoB does not depend on a formula that breaks down when triglycerides are high or LDL-C is very low [1].
Fasting does not change ApoB [5]. Even after a meal, more than 95 percent of circulating ApoB is ApoB-100 in people without severe hypertriglyceridemia [1]. The test counts ApoB-100 and ApoB-48 together.
The National Lipid Association describes the cost of running the test as low, but notes that some insurers still deny or restrict coverage [1]. Prices to patients vary by country, lab and plan.
For who should test, how results are reported and when to retest, see the ApoB test.
When an ApoB test adds the most
Standard lipid panel done. When does adding ApoB help most?
- Triglycerides above 133 mg/dL (1.5 mmol/L)1.5 mmol/L (133 mg/dL), or 200 mg/dL or moreAdd ApoB: Canada (CCS 2021) uses the first cut point, the 2018 AHA/ACC guideline the second
- Diabetes, obesity or metabolic syndromeAdd ApoB: LDL-C may understate particle number (ESC/EAS 2019)
- Very low LDL-C on treatmentAdd ApoB: LDL-C may understate particle number (ESC/EAS 2019)
- LDL-C and non-HDL-C at goal, residual risk suspectedUse ApoB selectively (ACC/AHA 2026)
- Suspected inherited lipid disorder or family screeningAdd ApoB to clarify a possible genetic disorder (NLA 2024)
- Starting or changing lipid-lowering therapyRepeat ApoB 4 to 12 weeks later (NLA 2024)
No fasting needed (EAS/EFLM 2016). Discuss any result, and whether to test at all, with your clinician.
What is a good ApoB level?
It depends on your cardiovascular risk. European guidelines set ApoB goals of under 100 mg/dL (1.0 g/L)1.0 g/L (100 mg/dL) at moderate risk, under 80 mg/dL (0.8 g/L)0.8 g/L (80 mg/dL) at high risk and under 65 mg/dL (0.65 g/L)0.65 g/L (65 mg/dL) at very high risk. The US flags 130 mg/dL (1.3 g/L)1.3 g/L (130 mg/dL) as a risk enhancer.
No guideline uses a single normal range for ApoB. Each one ties the number to your overall risk, which a clinician estimates from age, blood pressure, diabetes, smoking, family history and existing heart disease. The table below puts every major guideline's ApoB numbers in one place.
- ESC/EAS (Europe). ApoB goals of under 65, 80 and 100 mg/dL for very high, high and moderate risk, alongside LDL-C goals of under 55, 70 and 100 mg/dL [3]. The 2025 focused update kept ApoB as a secondary target [6].
- NLA (US lipid specialists). Suggested ApoB thresholds of 60, 70 and 90 mg/dL for very high, high and borderline to intermediate risk, chosen to match LDL-C thresholds of 55, 70 and 100 mg/dL [1].
- CCS (Canada). ApoB of 1.05 g/L or higher supports starting a statin at intermediate risk; 0.7 g/L or higher on a maximal statin supports adding ezetimibe or a PCSK9 inhibitor in people with heart disease [19].
- AHA/ACC (US). The 2018 guideline lists ApoB of 130 mg/dL or more as a risk-enhancing factor [4]. The 2026 guideline reintroduced goals for LDL-C, non-HDL-C and, in select cases, ApoB [20], and uses ApoB selectively to judge residual risk once LDL-C and non-HDL-C goals are met [6]. Check its recommendation tables for exact ApoB values [21].
For the full population distribution and what optimal means, see normal ApoB levels.
| Source | Who it applies to | ApoB (mg/dL) | ApoB (g/L) | Type | LDL-C counterpart |
|---|---|---|---|---|---|
| ESC/EAS 2019, kept in 2025 update | Very high risk | under 65 | under 0.65 | Goal | under 55 mg/dL (1.4 mmol/L)1.4 mmol/L (55 mg/dL) |
| ESC/EAS 2019 | High risk | under 80 | under 0.80 | Goal | under 70 mg/dL (1.8 mmol/L)1.8 mmol/L (70 mg/dL) |
| ESC/EAS 2019 | Moderate risk | under 100 | under 1.00 | Goal | under 100 mg/dL (2.6 mmol/L)2.6 mmol/L (100 mg/dL) |
| NLA 2024 | Very high risk | 60 | 0.60 | Consider intensifying | 55 mg/dL |
| NLA 2024 | High risk | 70 | 0.70 | Consider intensifying | 70 mg/dL |
| NLA 2024 | Borderline to intermediate risk | 90 | 0.90 | Consider intensifying | 100 mg/dL |
| CCS 2021 (Canada) | Heart disease, on maximal statin | 70 or higher | 0.70 or higher | Add ezetimibe or PCSK9 inhibitor | 1.8 mmol/L or higher |
| CCS 2021 (Canada) | Intermediate risk, primary prevention | 105 or higher | 1.05 or higher | Start a statin | 3.5 mmol/L or higher |
| CCS 2021 (Canada) | Low risk with a statin-indicated condition | 145 or higher | 1.45 or higher | Start a statin | 5.0 mmol/L or higher |
| AHA/ACC 2018 | Primary prevention | 130 or higher | 1.30 or higher | Risk-enhancing factor | about 160 mg/dL |
| EAS/EFLM 2016 | Lab reports | 100 or higher | 1.00 or higher | Flag as abnormal | 115 mg/dL (3 mmol/L)3 mmol/L (115 mg/dL) flag |
ApoB goals and cut points by guideline (mg/dL)
- Very high risk goal met
- 300.3 to 650.65
- Moderate risk goal met
- 650.65 to 1001
- Lab flag
- 1001 to 1301.3
- Risk enhancer
- 1301.3 to 1601.6
- 65 mg/dL0.65 g/L: ESC very high
- 80 mg/dL0.8 g/L: ESC high
- 100 mg/dL1 g/L: ESC moderate
- 130 mg/dL1.3 g/L: AHA/ACC
How is ApoB different from LDL cholesterol?
LDL-C measures how much cholesterol LDL particles carry; ApoB counts the particles themselves, including VLDL, IDL and Lp(a). Usually the two move together, but when they disagree, risk follows ApoB more closely.
In populations, ApoB, LDL-C and non-HDL-C are tightly correlated, above 0.90 in UK Biobank [22]. In individuals they can split apart. High triglycerides, obesity and insulin resistance tend to produce smaller, cholesterol-depleted LDL particles, which lowers LDL-C while ApoB stays high [1].
When the markers disagree, the extra particles matter. In statin-treated patients, ApoB above the median with LDL-C below it carried a hazard ratio of 1.49 for heart attack, while high LDL-C with low ApoB carried no extra risk [23]. Statins also lower ApoB less than LDL-C, 33 percent versus 42 percent on average, so LDL-C can look on target while particle count does not [24].
Non-HDL-C sits in between: it is the cholesterol in all ApoB particles and needs no extra test. The full comparison is on ApoB vs LDL cholesterol, and the Lp(a) comparison is on ApoB vs Lp(a). The LDL cholesterol and triglycerides hubs explain those markers on their own.
How ApoB, LDL-C and non-HDL-C relate
Particle down, What each test counts across
Chylomicron remnant (ApoB-48)
- LDL-CNot counted
- Non-HDL-CIts cholesterol
- ApoBOne particle
VLDL (ApoB-100)
- LDL-CNot counted
- Non-HDL-CIts cholesterol
- ApoBOne particle
IDL (ApoB-100)
- LDL-CIts cholesterol, in standard methods
- Non-HDL-CIts cholesterol
- ApoBOne particle
LDL (ApoB-100)
- LDL-CIts cholesterol
- Non-HDL-CIts cholesterol
- ApoBOne particle
Lp(a) (ApoB-100)
- LDL-CIts cholesterol, in standard methods
- Non-HDL-CIts cholesterol
- ApoBOne particle
HDL (no ApoB, not atherogenic)
- LDL-CNot counted
- Non-HDL-CNot counted
- ApoBNot counted
| LDL-C | Non-HDL-C | ApoB | |
|---|---|---|---|
| Chylomicron remnant (ApoB-48) | Not counted | Its cholesterol | One particle |
| VLDL (ApoB-100) | Not counted | Its cholesterol | One particle |
| IDL (ApoB-100) | Its cholesterol, in standard methods | Its cholesterol | One particle |
| LDL (ApoB-100) | Its cholesterol | Its cholesterol | One particle |
| Lp(a) (ApoB-100) | Its cholesterol, in standard methods | Its cholesterol | One particle |
| HDL (no ApoB, not atherogenic) | Not counted | Not counted | Not counted |
LDL makes up about 91% of ApoB particles and VLDL about 9% (Morze 2025); chylomicrons are typically under 1% (ESC/EAS 2019).
What raises and lowers ApoB?
Genes, diet, body weight, insulin resistance, some medications and some illnesses raise ApoB. Diet changes lower it by a few mg/dL each; medications lower it by roughly 14 to 50 percent.
What raises it. Inherited disorders such as familial hypercholesterolemia and familial combined hyperlipidemia; diets high in saturated fat [25]; obesity and insulin resistance [1]; new kidney, liver or thyroid disease; and some medications, including sex hormone therapy, thiazide diuretics, antiretroviral therapy and immunosuppressants [1]. Ketogenic diets raised ApoB by 35 mg/dL (0.35 g/L)0.35 g/L (35 mg/dL) in a small pooled analysis of normal-weight adults [26].
What lowers it. Food changes each lower ApoB by a few mg/dL: about 10 g a day of psyllium by 5 mg/dL [27], 3.5 g a day of oat beta-glucan by 3 mg/dL [28], walnuts by about 4 mg/dL [29]. Combined patterns such as the Portfolio diet go further [30]. Medications go further still: statins lower ApoB by about 33 percent [24], PCSK9 inhibitors by 43 to 50 percent [31] [32], and bempedoic acid by about 14 percent [33].
The full ranking, with every lever in one table, is on how to lower ApoB. In AumniVIDA, the longevity focus and Mediterranean pattern protocols track the saturated fat and fiber targets that move ApoB, and the keto and low-carb protocol keeps your lipid trend in view. Decisions about medication belong with your clinician.

What does the evidence not show yet?
ApoB is the best-supported measure of atherogenic particles, but no outcome trial has yet tested ApoB-guided treatment against LDL-C-guided treatment, and adding ApoB to standard risk scores barely changes who is classed as high risk.
- Little gain in population risk scores. In 165,544 people without heart disease, adding ApoB and ApoA-I to standard risk factors changed the C-index by only 0.0006 [34]. In UK Biobank the gain from adding ApoB to total and HDL cholesterol was 0.0004 [22]. ApoB earns its place mostly in individuals whose LDL-C understates their particle count, not as a universal screening upgrade.
- No ApoB-guided outcome trial. ApoB thresholds are derived from LDL-C trials and regression, because no completed trial used ApoB entry criteria [1]. ApoB-guided treatment has not been tested against conventional LDL-C-guided management in outcome trials [6].
- No agreed lifelong optimum. Guidelines set goals by short-term risk. Whether very low ApoB from early adulthood prevents more disease is inferred from genetics, where lifelong lower LDL tracks lower risk [13], not from trials that started in young adults.
- Contested special cases. A 2025 study of lean people on ketogenic diets that reported no link between ApoB and plaque growth was retracted in 2026 over methodological errors [35]. That leaves the question of whether diet-driven ApoB rises carry the same risk unanswered, not settled in either direction.
- One number cannot separate particle types. The routine test counts ApoB-100 and ApoB-48 together and cannot tell Lp(a) from LDL, so an Lp(a) test is still needed once [36].
The research
Foundational studies
The work that established what this marker means.
- 1986Complete protein sequence and identification of structural domains of human apolipoprotein BNatureThe full 4,563 amino acid sequence of ApoB-100 showed one very large protein that wraps each LDL particle and binds the LDL receptor.
- 1987A novel form of tissue-specific RNA processing produces apolipoprotein-B48 in intestineCellA single C to T change in intestinal RNA creates a stop signal at codon 2153, which is how the gut makes the shorter ApoB-48.
- 1987Familial defective apolipoprotein B-100: low density lipoproteins with abnormal receptor bindingProc Natl Acad Sci U S AThis study described familial defective ApoB-100, an inherited ApoB change that leaves LDL with about a third of normal receptor binding.
- 2001High apolipoprotein B, low apolipoprotein A-I, and improvement in the prediction of fatal myocardial infarction (AMORIS study): a prospective studyLancetIn the Swedish AMORIS cohort, ApoB predicted fatal heart attack more strongly than LDL cholesterol in both men and women.
- 2004Effect of potentially modifiable risk factors associated with myocardial infarction in 52 countries (the INTERHEART study): case-control studyLancetIn INTERHEART, across 52 countries, a high ApoB/ApoA1 ratio was the risk factor with the largest population attributable risk for heart attack.
- 2011A meta-analysis of low-density lipoprotein cholesterol, non-high-density lipoprotein cholesterol, and apolipoprotein B as markers of cardiovascular riskCirc Cardiovasc Qual OutcomesAcross 12 studies with 233,455 people, ApoB was the strongest lipid marker of cardiovascular risk, ahead of non-HDL-C and LDL-C.
- 2012Lipid-related markers and cardiovascular disease predictionJAMAIn 165,544 people from 37 cohorts, adding ApoB and ApoA-I to standard risk factors improved prediction only slightly.
- 2019Association of Triglyceride-Lowering LPL Variants and LDL-C-Lowering LDLR Variants With Risk of Coronary Heart DiseaseJAMAGenetic variants that lower triglycerides and variants that lower LDL-C cut heart disease risk by the same amount per 10 mg/dL lower ApoB.
- 2019Comparison of Conventional Lipoprotein Tests and Apolipoproteins in the Prediction of Cardiovascular DiseaseCirculationIn UK Biobank, ApoB, LDL-C and non-HDL-C carried similar risk per standard deviation, and adding ApoB to total and HDL cholesterol barely improved prediction.
- 2020Evaluating the relationship between circulating lipoprotein lipids and apolipoproteins with risk of coronary heart disease: A multivariable Mendelian randomisation analysisPLoS MedIn multivariable Mendelian randomization, ApoB was the lipid trait that explained the link between blood lipids and coronary heart disease.
- 2021Apolipoprotein B and Non-HDL Cholesterol Better Reflect Residual Risk Than LDL Cholesterol in Statin-Treated PatientsJ Am Coll CardiolIn statin-treated patients, high ApoB with low LDL-C carried a higher risk of heart attack and death, while high LDL-C with low ApoB did not.
- 2022Association of Apolipoprotein B-Containing Lipoproteins and Risk of Myocardial Infarction in Individuals With and Without Atherosclerosis: Distinguishing Between Particle Concentration, Type, and ContentJAMA CardiolIn UK Biobank, when ApoB, non-HDL-C and triglycerides were tested together, only ApoB stayed linked to heart attack risk.
Guidelines and reviews
Where expert bodies and systematic reviews have landed.
- 2008Differential response of cholesterol and particle measures of atherogenic lipoproteins to LDL-lowering therapy: implications for clinical practiceJ Clin LipidolAcross 11 studies with 17,035 people, statins lowered LDL-C by 42 percent but ApoB by only 33 percent on average.
- 2014Effect of dietary pulse intake on established therapeutic lipid targets for cardiovascular risk reduction: a systematic review and meta-analysis of randomized controlled trialsCMAJAbout one serving a day of beans, lentils or chickpeas lowered LDL-C by 0.17 mmol/L but did not change ApoB significantly.
- 2016Fasting is not routinely required for determination of a lipid profile: clinical and laboratory implications including flagging at desirable concentration cut-points-a joint consensus statement from the European Atherosclerosis Society and European Federation of Clinical Chemistry and Laboratory MedicineEur Heart JThe EAS and EFLM consensus found that fasting does not change ApoB and recommends that labs flag ApoB of 100 mg/dL (1.0 g/L)1.0 g/L (100 mg/dL) or higher.
- 2016The effect of oat β-glucan on LDL-cholesterol, non-HDL-cholesterol and apoB for CVD risk reduction: a systematic review and meta-analysis of randomised-controlled trialsBr J NutrAbout 3.5 g a day of oat beta-glucan lowered ApoB by 3 mg/dL (0.03 g/L)0.03 g/L (3 mg/dL) across 58 trials.
- 2017Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus PanelEur Heart JThe EAS consensus panel concluded from over 200 studies with more than 2 million people that LDL causes atherosclerotic cardiovascular disease, in proportion to dose and duration.
- 2018Effect of psyllium (Plantago ovata) fiber on LDL cholesterol and alternative lipid targets, non-HDL cholesterol and apolipoprotein B: a systematic review and meta-analysis of randomized controlled trialsAm J Clin NutrAbout 10 g a day of psyllium lowered ApoB by 5 mg/dL (0.05 g/L)0.05 g/L (5 mg/dL) across 28 trials.
- 2018Portfolio Dietary Pattern and Cardiovascular Disease: A Systematic Review and Meta-analysis of Controlled TrialsProg Cardiovasc DisThe Portfolio diet of nuts, plant protein, viscous fiber and plant sterols lowered LDL-C by about 17 percent and also lowered ApoB.
- 2018Effects of walnut consumption on blood lipids and other cardiovascular risk factors: an updated meta-analysis and systematic review of controlled trialsAm J Clin NutrWalnut-enriched diets lowered ApoB by 3.7 mg/dL compared with control diets across 26 trials.
- 20192018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice GuidelinesCirculationThe 2018 AHA/ACC cholesterol guideline lists ApoB of 130 mg/dL or higher as a risk-enhancing factor, equivalent to LDL-C of about 160 mg/dL.
- 2019Apolipoprotein B Particles and Cardiovascular Disease: A Narrative ReviewJAMA CardiolThis review explains that cholesterol enters the artery wall only inside ApoB particles, so the number of particles drives how many get trapped.
- 20202019 ESC/EAS Guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular riskEur Heart JThe 2019 ESC/EAS guideline set ApoB goals of under 65, 80 and 100 mg/dL for very high, high and moderate risk, recommends ApoB when triglycerides are high, and says fasting is not required.
- 20212021 Canadian Cardiovascular Society Guidelines for the Management of Dyslipidemia for the Prevention of Cardiovascular Disease in AdultsCan J CardiolThe 2021 Canadian guideline prefers ApoB or non-HDL-C over LDL-C when triglycerides exceed 1.5 mmol/L and gives ApoB thresholds of 1.05, 1.45 and 0.7 g/L for treatment decisions.
- 2021Effect of Bempedoic Acid on atherogenic lipids and inflammation: A meta-analysisClin Investig ArteriosclerAcross seven trials, bempedoic acid lowered ApoB by about 14 percent and LDL-C by about 20 percent versus placebo.
- 2023Effects of very low-carbohydrate ketogenic diets on lipid profiles in normal-weight (body mass index < 25 kg/m2) adults: a meta-analysisNutr RevIn three trials of normal-weight adults, ketogenic diets raised ApoB by 35 mg/dL (0.35 g/L)0.35 g/L (35 mg/dL) compared with control diets.
- 2024Role of apolipoprotein B in the clinical management of cardiovascular risk in adults: An Expert Clinical Consensus from the National Lipid AssociationJ Clin LipidolThe National Lipid Association consensus explains that each atherogenic particle carries one ApoB, publishes US population percentiles, and suggests ApoB thresholds of 60, 70 and 90 mg/dL by risk.
- 20252025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemiasEur Heart JThe 2025 ESC/EAS focused update recommends measuring Lp(a) at least once in every adult, treats Lp(a) above 50 mg/dL (105 nmol/L) as a risk modifier, and does not support supplements without proven LDL-lowering efficacy.
- 20262026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice GuidelinesCirculationThe 2026 ACC/AHA multisociety guideline replaces the 2018 cholesterol guideline and covers LDL-C, non-HDL-C, ApoB, Lp(a) and triglycerides.
Recent research
Notable work from the last three years.
- 2024Lipoprotein(a) Is Markedly More Atherogenic Than LDL: An Apolipoprotein B-Based Genetic AnalysisJ Am Coll CardiolGenetic analysis estimated that an Lp(a) particle is about 6 times as atherogenic as an LDL particle.
- 2025ApoB-containing lipoproteins: count, type, size, and risk of coronary artery diseaseEur Heart JTotal ApoB particle count captured lipid-related coronary risk regardless of particle type or size, and Lp(a) added risk on top.
- 2026Primary Prevention of Dyslipidemia: 10 Practice-Changing Takeaways from the 2026 ACC/AHA Multisociety GuidelineCurr Atheroscler RepThis summary of the 2026 ACC/AHA guideline highlights lipid screening every 5 years after age 19, Lp(a) once, selective ApoB testing, and goals for LDL-C, non-HDL-C and ApoB in select cases.
- 2026The 2026 ACC/AHA Dyslipidemia Guideline: A Critical and Transatlantic Perspective on Personalized Lipid ManagementLife (Basel)This review of the 2026 ACC/AHA guideline notes selective ApoB testing for residual risk and that ApoB-guided treatment has not been tested in outcome trials.
- 2026The lipid lowering efficacy of PCSK9 inhibitors alone vs. statins alone: a meta-analysisFront Cardiovasc MedPCSK9 inhibitor monotherapy lowered ApoB by 43 percent compared with 33 percent for high-intensity statins.
- 2026Efficacy and Safety of Oral PCSK9 Inhibitors: Insights from a Meta-analysis of RCTSEur J Prev CardiolAcross five trials, oral PCSK9 inhibitors lowered LDL-C by 59 percent and ApoB by 50 percent versus placebo.
- 2026Inclisiran in Patients with CKD: Post Hoc Pooled Analysis of Three Phase 3 TrialsJ Am Soc NephrolPooled phase 3 trials of inclisiran showed about 50 percent LDL-C lowering, with lower ApoB, across levels of kidney function.
- 2026Retraction: Longitudinal Data from the KETO-CTA Study: Plaque Predicts Plaque, ApoB Does NotJACC AdvJACC: Advances retracted the KETO-CTA follow-up paper that reported no link between ApoB and plaque progression, citing methodological errors.
What well-known voices say about ApoB
Their positions, summarized in our words. Follow each link for the full context.
Peter AttiaPhysician, host of The Drive podcast and author of Outlive
Argues for lowering ApoB early in life and well below guideline goals. He has said he sees no reason for ApoB above about 60 mg/dL, would like people below the 5th percentile, and uses medication, including a statin with a PCSK9 inhibitor in his own case, to get there.
Allan SnidermanCardiologist and ApoB researcher at McGill University
Has spent decades arguing that ApoB is a better marker of vascular risk than LDL cholesterol, because the number of particles decides how many get trapped in the artery wall. He favors causal, 30-year risk models over 10-year scores so prevention can start earlier.
The Drive #185: Cardiovascular disease and why we should change the way we assess risk
G. Michael AllanFamily physician and co-author of the CFPC Tools for Practice evidence summaries
Takes the skeptical primary-care view: in people without heart disease, adding ApoB to standard risk factors barely changes risk prediction, so clinicians should use risk calculators and proven therapies. The summary notes Canada's guideline still prefers ApoB or non-HDL-C when triglycerides are high.
Tools for Practice #343: non-traditional lipoproteins for cardiovascular risk
Watch
Talks and explainers worth your time. Nothing loads from YouTube until you press play.
ApoB, LDL-C, Lp(a), and insulin as risk factors for cardiovascular disease [AMA 43 sneak peek]
Peter Attia MDPeter Attia MD@peterattiamdSubscribers1MStartedJuly 2015CountryNot statedVideos1.8KTotal views137.4MNew videos, last 30 days7New videos, last year105From YouTube, 2026-10-31Open on YouTube
Attia compares ApoB with LDL-C, Lp(a) and insulin as risk markers on his own channel.
What Should Your ApoB Levels Be for Optimal Heart Health? | Thomas Dayspring | The Proof EP #315
The Proof with Simon HillThe Proof with Simon Hill@theproofwithsimonhillSubscribers149KStartedNovember 2011CountryUnited StatesVideos2.2KTotal views23.1MNew videos, last 30 days44New videos, last year368From YouTube, 2026-10-31Open on YouTube
Lipidologist Thomas Dayspring discusses ApoB targets in a long-form interview.
Peter Attia on the INSANE Longevity Benefits of Low ApoB (how to lower ApoB with diet)
FoundMyFitness ClipsFoundMyFitness Clips@foundmyfitnessclipsSubscribers554KStartedJanuary 2019CountryUnited StatesVideos2.1KTotal views161.7MNew videos, last 30 days38New videos, last year423From YouTube, 2026-10-31Open on YouTube
A clip from Rhonda Patrick's podcast on why Attia targets low ApoB and the role of diet.
How to Lower Your ApoB (Lifestyle, Diet, & Medication)
Jeremy London, MDJeremy London, MD@drjeremylondonSubscribers408KStartedFebruary 2024CountryUnited StatesVideos609Total views118.4MNew videos, last 30 days18New videos, last year211From YouTube, 2026-10-31Open on YouTube
A physician walks through lifestyle, diet and medication options for lowering ApoB.
#240 Dr. Spencer Nadolsky on Repatha, ApoB Targets, and What Actually Matters in Lipidology
Dr. Mike HartDr. Mike Hart@drmikehartmdSubscribers6KStartedMarch 2011CountryCanadaVideos934Total views1MNew videos, last 30 days29New videos, last year287From YouTube, 2026-10-31Open on YouTube
Physician Spencer Nadolsky covers ApoB targets and PCSK9 therapy from a clinical view.
Protocols that act on ApoB
- Outlive and Medicine 3.0 (Peter Attia)Outlive is physician Peter Attia's 2023 book on Medicine 3.0, a prevention-first approach to longevity.
- Mediterranean dietThe Mediterranean diet is an eating pattern built on vegetables, fruit, legumes, whole grains, nuts, fish and olive oil as the main fat, with little red or processed meat, butter or sweets.
- Outlive and Medicine 3.0 (Peter Attia)Outlive is physician Peter Attia's 2023 book on Medicine 3.0, a prevention-first approach to longevity.
- Ketogenic dietA ketogenic diet keeps carbohydrate under about 20 to 50 g a day so the body burns fat and makes ketones, defined in supervised programs as blood BHB of 0.5 to 3.0 mmol/L.
Common questions
What does ApoB stand for?
Is ApoB included in a standard lipid panel?
Usually not. A standard panel measures total cholesterol, HDL-C and triglycerides and calculates LDL-C and non-HDL-C. ApoB is a separate test your clinician adds, which is why the National Lipid Association calls for wider access and coverage [1].
Is ApoB genetic?
Partly. Inherited conditions such as familial hypercholesterolemia, including familial defective ApoB-100 [9], and familial combined hyperlipidemia cause high ApoB. The NLA suggests using ApoB to help screen family members when a genetic lipid disorder is suspected [1]. Diet, weight and other conditions still move it.
Can ApoB be too low?
What is the ApoB/ApoA1 ratio?
It divides the atherogenic particle protein (ApoB) by the main HDL protein (ApoA1). In INTERHEART, the top fifth of the ratio carried 3.25 times the heart attack odds of the bottom fifth [18]. Current guidelines focus on ApoB itself rather than the ratio.
Does ApoB include Lp(a)?
Yes. Each Lp(a) particle carries one ApoB-100, so it is counted in your ApoB result [5]. Lp(a) is usually a small share of the total, so a normal ApoB does not rule out high Lp(a). See ApoB vs Lp(a).
Can ApoB be higher than LDL cholesterol?
The numbers are not directly comparable because one counts particles and the other weighs cholesterol, but ApoB can be high relative to LDL-C. That pattern is common with high triglycerides, obesity and insulin resistance [1]. See ApoB vs LDL.
How do I convert ApoB from g/L to mg/dL?
Multiply g/L by 100. An ApoB of 0.8 g/L is 80 mg/dL, and 1.2 g/L is 120 mg/dL. Research papers sometimes use nmol/L; in UK Biobank a mean of 1.03 g/L corresponded to about 1,870 nmol/L [11].
Sources
- 1.Soffer DE, Marston NA, Maki KC, et al. Role of apolipoprotein B in the clinical management of cardiovascular risk in adults: An Expert Clinical Consensus from the National Lipid Association. J Clin Lipidol, 2024. doi:10.1016/j.jacl.2024.08.013
- 2.Ference BA, Kastelein JJP, Ray KK, et al. Association of Triglyceride-Lowering LPL Variants and LDL-C-Lowering LDLR Variants With Risk of Coronary Heart Disease. JAMA, 2019. doi:10.1001/jama.2018.20045
- 3.Mach F, Baigent C, Catapano AL, et al. 2019 ESC/EAS Guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular risk. Eur Heart J, 2020. doi:10.1093/eurheartj/ehz455
- 4.Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation, 2019. doi:10.1161/CIR.0000000000000625
- 5.Nordestgaard BG, Langsted A, Mora S, et al. Fasting is not routinely required for determination of a lipid profile: clinical and laboratory implications including flagging at desirable concentration cut-points-a joint consensus statement from the European Atherosclerosis Society and European Federation of Clinical Chemistry and Laboratory Medicine. Eur Heart J, 2016. doi:10.1093/eurheartj/ehw152
- 6.Sabouret P, Mafrica D, Giamundo DM, et al. The 2026 ACC/AHA Dyslipidemia Guideline: A Critical and Transatlantic Perspective on Personalized Lipid Management. Life (Basel), 2026. doi:10.3390/life16091470
- 7.Knott TJ, Pease RJ, Powell LM, et al. Complete protein sequence and identification of structural domains of human apolipoprotein B. Nature, 1986. doi:10.1038/323734a0
- 8.Powell LM, Wallis SC, Pease RJ, et al. A novel form of tissue-specific RNA processing produces apolipoprotein-B48 in intestine. Cell, 1987. doi:10.1016/0092-8674(87)90510-1
- 9.Innerarity TL, Weisgraber KH, Arnold KS, et al. Familial defective apolipoprotein B-100: low density lipoproteins with abnormal receptor binding. Proc Natl Acad Sci U S A, 1987. doi:10.1073/pnas.84.19.6919
- 10.Morze J, Melloni GEM, Wittenbecher C, et al. ApoB-containing lipoproteins: count, type, size, and risk of coronary artery disease. Eur Heart J, 2025. doi:10.1093/eurheartj/ehaf207
- 11.Björnson E, Adiels M, Taskinen MR, et al. Lipoprotein(a) Is Markedly More Atherogenic Than LDL: An Apolipoprotein B-Based Genetic Analysis. J Am Coll Cardiol, 2024. doi:10.1016/j.jacc.2023.10.039
- 12.Sniderman AD, Thanassoulis G, Glavinovic T, et al. Apolipoprotein B Particles and Cardiovascular Disease: A Narrative Review. JAMA Cardiol, 2019. doi:10.1001/jamacardio.2019.3780
- 13.Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J, 2017. doi:10.1093/eurheartj/ehx144
- 14.Richardson TG, Sanderson E, Palmer TM, et al. Evaluating the relationship between circulating lipoprotein lipids and apolipoproteins with risk of coronary heart disease: A multivariable Mendelian randomisation analysis. PLoS Med, 2020. doi:10.1371/journal.pmed.1003062
- 15.Sniderman AD, Williams K, Contois JH, et al. A meta-analysis of low-density lipoprotein cholesterol, non-high-density lipoprotein cholesterol, and apolipoprotein B as markers of cardiovascular risk. Circ Cardiovasc Qual Outcomes, 2011. doi:10.1161/CIRCOUTCOMES.110.959247
- 16.Marston NA, Giugliano RP, Melloni GEM, et al. Association of Apolipoprotein B-Containing Lipoproteins and Risk of Myocardial Infarction in Individuals With and Without Atherosclerosis: Distinguishing Between Particle Concentration, Type, and Content. JAMA Cardiol, 2022. doi:10.1001/jamacardio.2021.5083
- 17.Walldius G, Jungner I, Holme I, et al. High apolipoprotein B, low apolipoprotein A-I, and improvement in the prediction of fatal myocardial infarction (AMORIS study): a prospective study. Lancet, 2001. doi:10.1016/S0140-6736(01)07098-2
- 18.Yusuf S, Hawken S, Ounpuu S, et al. Effect of potentially modifiable risk factors associated with myocardial infarction in 52 countries (the INTERHEART study): case-control study. Lancet, 2004. doi:10.1016/S0140-6736(04)17018-9
- 19.Pearson GJ, Thanassoulis G, Anderson TJ, et al. 2021 Canadian Cardiovascular Society Guidelines for the Management of Dyslipidemia for the Prevention of Cardiovascular Disease in Adults. Can J Cardiol, 2021. doi:10.1016/j.cjca.2021.03.016
- 20.Abramov D, Minhas AMK, Shapiro MD, et al. Primary Prevention of Dyslipidemia: 10 Practice-Changing Takeaways from the 2026 ACC/AHA Multisociety Guideline. Curr Atheroscler Rep, 2026. doi:10.1007/s11883-026-01437-9
- 21.Writing Committee Members; Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation, 2026. doi:10.1161/CIR.0000000000001423
- 22.Welsh C, Celis-Morales CA, Brown R, et al. Comparison of Conventional Lipoprotein Tests and Apolipoproteins in the Prediction of Cardiovascular Disease. Circulation, 2019. doi:10.1161/CIRCULATIONAHA.119.041149
- 23.Johannesen CDL, Mortensen MB, Langsted A, et al. Apolipoprotein B and Non-HDL Cholesterol Better Reflect Residual Risk Than LDL Cholesterol in Statin-Treated Patients. J Am Coll Cardiol, 2021. doi:10.1016/j.jacc.2021.01.027
- 24.Sniderman AD. Differential response of cholesterol and particle measures of atherogenic lipoproteins to LDL-lowering therapy: implications for clinical practice. J Clin Lipidol, 2008. doi:10.1016/j.jacl.2007.12.006
- 25.Bergeron N, Chiu S, Williams PT, et al. Effects of red meat, white meat, and nonmeat protein sources on atherogenic lipoprotein measures in the context of low compared with high saturated fat intake: a randomized controlled trial. Am J Clin Nutr, 2019. doi:10.1093/ajcn/nqz035
- 26.Joo M, Moon S, Lee YS, et al. Effects of very low-carbohydrate ketogenic diets on lipid profiles in normal-weight (body mass index < 25 kg/m2) adults: a meta-analysis. Nutr Rev, 2023. doi:10.1093/nutrit/nuad017
- 27.Jovanovski E, Yashpal S, Komishon A, et al. Effect of psyllium (Plantago ovata) fiber on LDL cholesterol and alternative lipid targets, non-HDL cholesterol and apolipoprotein B: a systematic review and meta-analysis of randomized controlled trials. Am J Clin Nutr, 2018. doi:10.1093/ajcn/nqy115
- 28.Ho HV, Sievenpiper JL, Zurbau A, et al. The effect of oat β-glucan on LDL-cholesterol, non-HDL-cholesterol and apoB for CVD risk reduction: a systematic review and meta-analysis of randomised-controlled trials. Br J Nutr, 2016. doi:10.1017/S000711451600341X
- 29.Guasch-Ferré M, Li J, Hu FB, et al. Effects of walnut consumption on blood lipids and other cardiovascular risk factors: an updated meta-analysis and systematic review of controlled trials. Am J Clin Nutr, 2018. doi:10.1093/ajcn/nqy091
- 30.Chiavaroli L, Nishi SK, Khan TA, et al. Portfolio Dietary Pattern and Cardiovascular Disease: A Systematic Review and Meta-analysis of Controlled Trials. Prog Cardiovasc Dis, 2018. doi:10.1016/j.pcad.2018.05.004
- 31.Kyan K, Gornbein J, Saver J. The lipid lowering efficacy of PCSK9 inhibitors alone vs. statins alone: a meta-analysis. Front Cardiovasc Med, 2026. doi:10.3389/fcvm.2026.1769430
- 32.Olmastroni E, Xie S, Galimberti F, et al. Efficacy and Safety of Oral PCSK9 Inhibitors: Insights from a Meta-analysis of RCTS. Eur J Prev Cardiol, 2026. doi:10.1093/eurjpc/zwag273
- 33.Masson W, Lobo M, Lavalle-Cobo A, et al. Effect of Bempedoic Acid on atherogenic lipids and inflammation: A meta-analysis. Clin Investig Arterioscler, 2021. doi:10.1016/j.arteri.2020.09.002
- 34.Emerging Risk Factors Collaboration; Di Angelantonio E, Gao P, Pennells L, et al. Lipid-related markers and cardiovascular disease prediction. JAMA, 2012. doi:10.1001/jama.2012.6571
- 35.Soto-Mota A, Norwitz NG, Manubolu VS, et al. Retraction: Longitudinal Data from the KETO-CTA Study: Plaque Predicts Plaque, ApoB Does Not. JACC Adv, 2026. doi:10.1016/j.jacadv.2026.102824
- 36.Mach F, Koskinas KC, Roeters van Lennep JE, et al. 2025 Focused Update of the 2019 ESC/EAS Guidelines for the management of dyslipidaemias. Eur Heart J, 2025. doi:10.1093/eurheartj/ehaf190
- 37.Landmesser U, Ray KK, Raal FJ, et al. Inclisiran in Patients with CKD: Post Hoc Pooled Analysis of Three Phase 3 Trials. J Am Soc Nephrol, 2026. doi:10.1681/ASN.0000001006
- 38.Solá R, Fitó M, Estruch R, et al. Effect of a traditional Mediterranean diet on apolipoproteins B, A-I, and their ratio: a randomized, controlled trial. Atherosclerosis, 2011. doi:10.1016/j.atherosclerosis.2011.04.026
- 39.Ha V, Sievenpiper JL, de Souza RJ, et al. Effect of dietary pulse intake on established therapeutic lipid targets for cardiovascular risk reduction: a systematic review and meta-analysis of randomized controlled trials. CMAJ, 2014. doi:10.1503/cmaj.131727